










Issue 101. I am starting the next hundred with what we get wrong about longevity medicine.
Not exactly a summer newsletter… no 120 tips.
What I heard. This year I met physicians, scientists, entrepreneurs and patients across the world. Everyone is talking about longevity. The enthusiasts and the skeptics, in the same room, using the same word to mean different things.
What I saw. An explosion of products, services and clinics, from Italy to Shanghai. Almost no way to tell which ones actually work. And a growing number of people who no longer trust the science at all.
What I feel. Longevity medicine is being led by platforms, influencers, and physicians are being left behind. We have the knowledge. We are losing the authority.
And I am optimistic because this is the beginning of a new era, driven by people who decided that they will be in charge of their longevity.
As always, Happy Sunday.
Dr. David Luu, Founder, longevity docs.™
Each week, I try to explore one idea that could advance longevity medicine and hopefully support physicians in bringing it to life.
Written for your patients. Feel free to forward it to them.
I have spent this year in a lot of different countries, different cities, different rooms. Same questions every time.
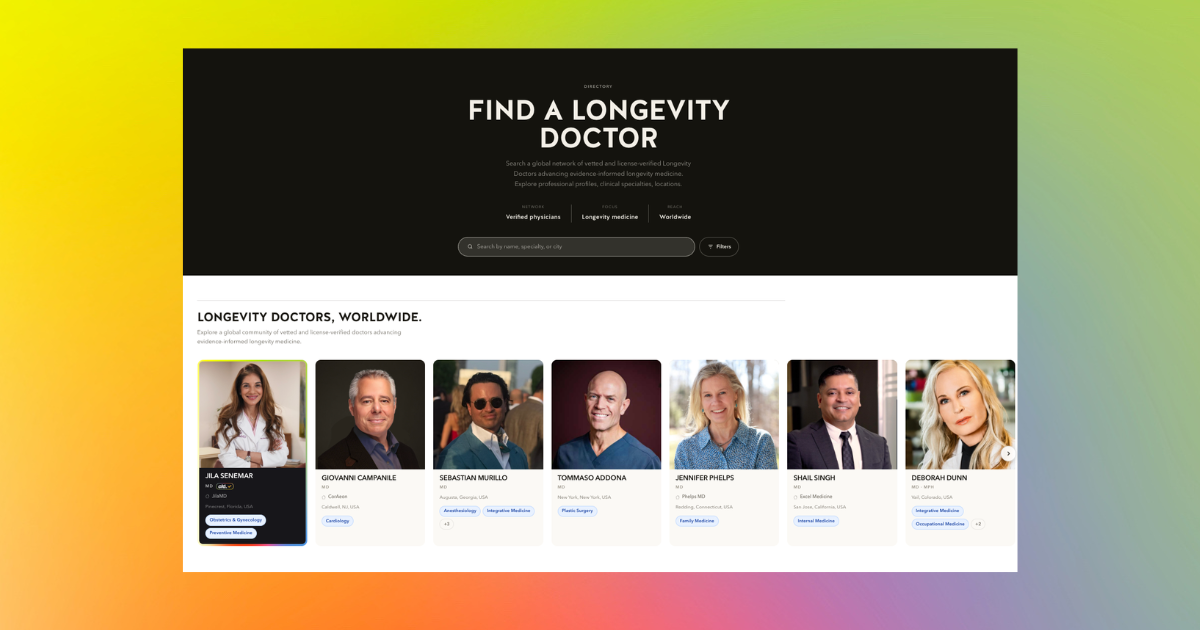
What does longevity actually mean? Where do I find a good doctor? What do you think about GLP-1s, Brian Johnson, Huberman, Sinclair, BPC-157, peptides, NAD? Who is the best doctor, the best clinic, the best test?
Longevity has gone mainstream. It does not matter where you are in the world or what you earn. Everyone is interested. Everyone is talking about it. It is the new status, and it is here to stay.
People come in through whatever door is closest to them. Beauty. Sleep. Wearables. Weight loss. Diet. A full-body MRI they saw on a podcast.
Then they get lost.
Ten things people get wrong, from the believers to the skeptics
- Longevity means living forever. It does not. It means more years where your body still works, and you are enjoying your life.
- Longevity is a panel of tests. Bloodwork, genomics, microbiome, full-body scan. Testing is not care. A result you cannot act on is a number, not a plan.
- Longevity is diet, sleep and exercise. These matter enormously. They are the floor, not the ceiling.
- Longevity is biohacking. Biohacking is n-of-1 with no control group and nobody accountable for the outcome.
- Longevity is intervention. Peptides, hyperbaric chambers, sauna. Interventions are tools. Tools are not a strategy.
- Longevity drugs already exist. They do not, not in the way people mean.
- Longevity is genetics. Your genome loads the gun. It is not the only thing pulling the trigger.
- The right stack will do it. No supplement combination has ever been shown to extend human lifespan.
- AI knows better than my doctor. So I will order my own labs and find my own drugs online.
- We are all going to die anyway, so let me enjoy my life. My grandfather smoked until 95 and he was fine. Maybe. You are not your grandfather, and survivorship bias is not a health plan.
The problem is not the evidence. It is the interpretation.
There is more longevity research published now than any physician can read. That is not the bottleneck. The bottleneck is who translates it.
Right now that job falls to media articles, influencer content, and scientific papers most people cannot parse. Self-appointed gurus. Brands explaining the thing they are selling. A few excellent physicians, drowned out.
One diet study in mice becomes a viral claim that protein is bad for you. Nobody reads the paper. Everybody shares the reel.
Meanwhile the people who actually know are in clinic or in the lab. Physicians and scientists are not trained to communicate at the speed the internet demands. So the loudest voice wins, and the loudest voice is usually selling something.
Longevity medicine is network intelligence
There is a deeper problem than bad information. Longevity medicine does not work as a list of facts.
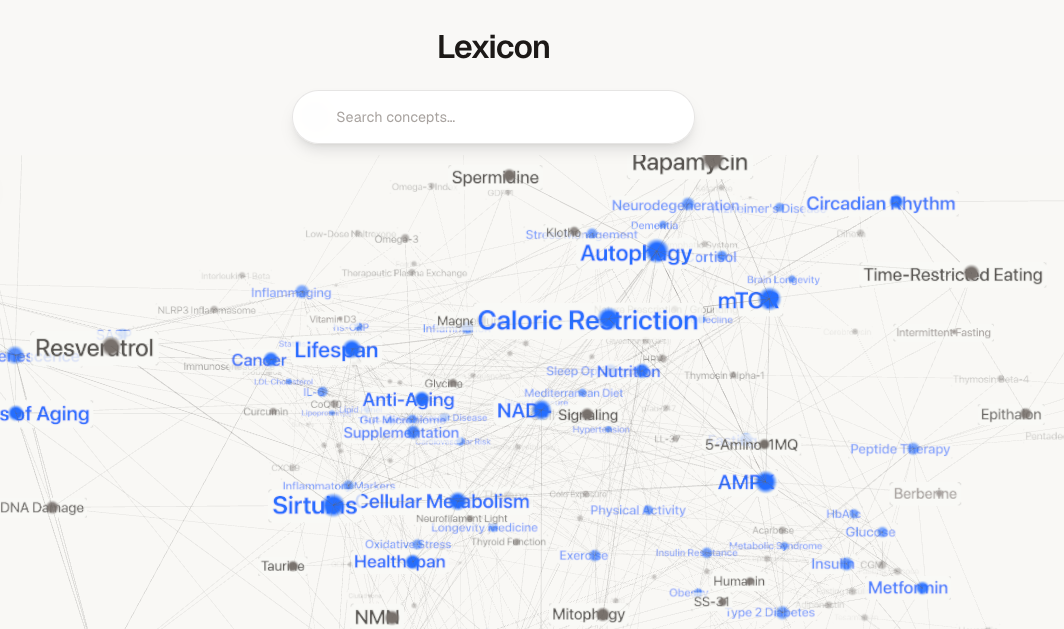
ApoB does not sit by itself. It connects to the lipid panel, to PCSK9 inhibitors, to oxidized LDL, to cardiovascular risk, to atherosclerosis, and out from there to inflammation, to hs-CRP, to IL-6.
Search any one of those terms and you get an article about that term. That is not how the biology works, and it is not how a good physician thinks. Your doctor is not looking up a definition. She is holding a map.
That map is what patients have never had access to. We believe longevity should be a human right. Which means the education has to reach everyone.
Originally published in The Longevity Medicine Intelligence newsletter (#101).

